Measles in Samoa: Thank the anti-vaccination lobby

The manner in which members of the anti-vaccination lobby have leapt upon the measles tragedy in Samoa identifies their awful, predatory cult quite well.

To completely understand why anti-vaccine activists promote such intellectually vicious lies and indeed hatred regarding an epidemic that Samoa has labelled a state of emergency I’d argue we need to first look back. Back to July last year when headlines reported the deaths of two infants following the MMR vaccination. Or rather, what we now know was thought to be MMR vaccine. We need to look back dear reader because antivaccinationists reacted in an “I told ya so” manner that was almost glee.

Despite there never being a recorded death due to vaccination or a vaccine in Australia, anti-vax profiteers who have peddled lies for years contend that death and disability after vaccination not only happens but are widespread. A vaccinologist was quoted in evidence to the No Jab No Pay Bill hearing that in Australian injuries serious enough to require compensation range between zero and five per year. I do apologise for referring to that occasion yet again. I also recommend the government publication Questions About Vaccination.

We must look back because regrettably it was the bogus causation peddled by anti-vax identities that gave them the confidence to begin commenting on this measles outbreak that hit Samoa in October this year (2019). As for facts, genuine health professionals and epidemiologists would be familiar with adulterated, out of date and counterfeit medications and vaccines causing harm in nations with health systems and infrastructure less developed than in New Zealand or Australia. Yet these events occur far less today due to safety procedures instigated across the globe.

Following investigations into the infant deaths in Samoa evidence was collated concluding “a tragic outcome from error preparing MMR vaccine”. The Immunisation Advisory Centre of New Zealand reports;

On 4 June 2019, both nurses pleaded guilty to negligence causing manslaughter. On 2 August, both nurses were sentenced to five years in prison. During the sentencing hearing, it was confirmed that one of the nurses mixed the MMR vaccine powder with expired muscle relaxant anaesthetic instead of water for injection supplied in a vial with the vaccine. Eight Samoan speaking New Zealand nurses visited Samoa in June to provide training for vaccinating nurses at district hospitals.

The same reference informs us there has never been a death associated with this vaccine in N.Z. It also has a helpful timeline and includes under August 3rd;

Report on RNZ website: The two nurses, who pleaded guilty to negligence causing the manslaughter of two infants, have been sentenced to five years in prison.

The Samoa Observer published a detailed account of the sentencing hearing, where it was confirmed that one of the nurses mixed the MMR vaccine powder with expired muscle relaxant anaesthetic instead of water for injection supplied in a vial with the vaccine.

The entire event effected parent confidence in immunisation. These doubts were magnified by antivaccinationists resulting in a further realisation of their aim: a reduction in vaccination. The Guardian recently reported that the WHO blames the “anti-vaccine scare” for the rise in cases and of course deaths. Kate O’Brien, director of the WHO immunisation department stressed that the rapid spread of measles in Samoa was due to the “very low coverage” of immunisation.

This resulted in the temporary suspension of the country’s immunisation programme and dented parents’ trust in the vaccine, even though it later turned out the deaths were caused by other medicines that were incorrectly administered.

O’Brien said that an anti-vaccine group had been stoking these fears further with a social media campaign, lamenting that “this is now being measured in the lives of children who have died in the course of this outbreak”.

Misinformation about the safety of vaccines, she said, “has had a very remarkable impact on the immunisation programme” in Samoa.

At least 42 fatalities can be attributed to this measles epidemic at time of writing. In the video below anti-vaxxer identity Taylor Winterstein is mentioned as having visited Samoa in June with diehard anti-vaxxer Robert Kennedy Jnr. Winterstein described herself as “pro-science” the narrator tells us. Oh, my.

Please spend some time reading up on this woman who is presently making a living scamming Wellness devotees and the ill out of their money.

Given the harrowing situation in Samoa and the speed at which measles morbidity and mortality is increasing the government has made the measles vaccine compulsory and warned those preventing community members from being vaccinated to stop.

Such as Fritz Alaiasa Neufelt, the oh-so-savvy businessman selling filtered tap water as the measles fighting “Kangen Water”. Lying as he plays with the lives of ill Samoans he claims that after a spray of his magic water;

“They’re feeling good,” he said. “The measles are already … not cured, but it’s already back to normal”.

The ABC recently reported that the “pro-science” Winterstein was a tad concerned about the governments position. No, not the position of vile Fritz spraying measles sufferers like office plants but the government.

In fact her rational, objective, pro-science mind has applied Godwin’s Law. The ABC cite her calm demeanor;

… Australian-Samoan influencer Taylor Winterstein made recent posts on Facebook and Instagram comparing Samoa’s compulsory vaccination program as akin to “Nazi Germany”.

“Forcing a medical procedure on an entire country, especially one that is proving to be ineffective, dangerous and making the virus more deadly, is straight up barbaric,” she wrote on Facebook.

So um, check it out, right. A “pro-science”, so-called “influencer” who peddles herself as a health guru has a tantrum claiming that the only known safe and effective preventative for measles is “proving to be ineffective, dangerous and making the virus more deadly”. And yeah, Nazi Germany. Pfft. Oh I’m influenced Tay. Trust me.

I’d say you can’t make this stuff up but that’s exactly what they do. Consider the increase in cases below and the time frame it covers.
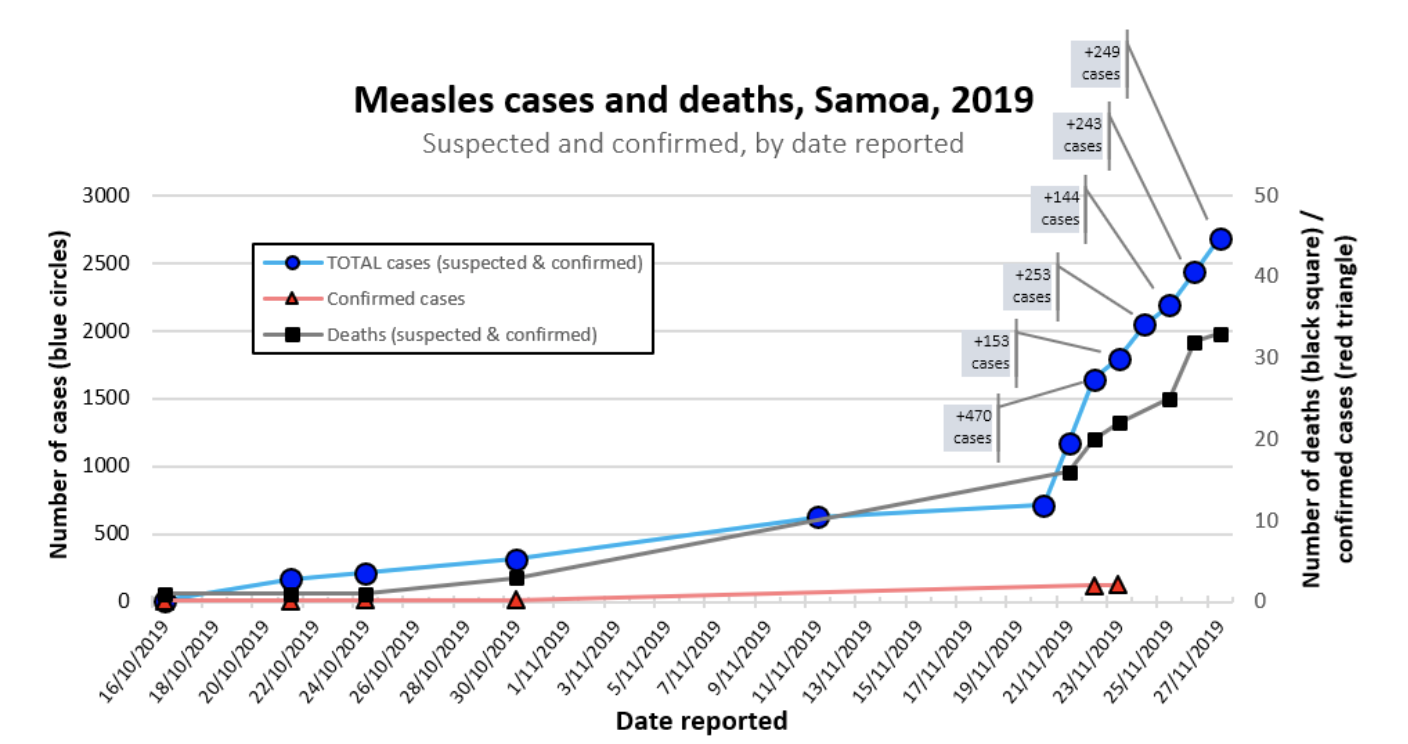
© Source: virologydownunder.com

Data: Samoan Government Facebook and Ministry of Health websites and media comments. Last update 27/11/19

Preparation: Ian M. Mackay, PhD

Immunisation rates were previously far higher in Samoa. Four years ago MMR coverage was 84%. By 2017 it had already dropped to 60%. Last year (2018) it had fallen to 31%.

There is no doubt. A drop in MMR vaccination has brought Samoa to a tragedy of shocking proportions. Two doses of MMR is the recommended, clearly life saving, dose.

But still, Meryl Dorey of The Australian Vaccination Risks Network tweeted this dishonest evidence free nonsense (left) just recently. Just as Winterstein pushes the piffle that the vaccine makes the virus more deadly, Dorey tries to convince her cult that malpractice is the cause.

I would urge Meryl Dorey to have another look above at the facts and follow some of the links. Revisit what is known about these deaths. Understand that it was not the expected MMR vaccine they received before dying.

Accept two nurses are now serving five years in prison for negligence. Know it was a negligent error in preparing the adulterated mixture that led to the deaths, then an eight month suspension of MMR. Admit the facts, admit the reality. Stop your lies.

Stop your negligence.

International Overdose Awareness Day – August 31st

Time To Remember                                  Time To Act


August 31st is International Overdose Awareness Day.

Access the IOAD link above to find an activity, get resources or make a donation. On the main page just under a couple of videos, we read;

International Overdose Awareness Day is a global event held on 31 August each year and aims to raise awareness of overdose and reduce the stigma of a drug-related death. It also acknowledges the grief felt by families and friends remembering those who have died or had a permanent injury as a result of drug overdose.

International Overdose Awareness Day spreads the message that the tragedy of overdose death is preventable.

Thousands of people die each year from drug overdose. They come from all walks of life.

Do you recognise the signs and symptoms of overdose? What is the impact of drug use and overdose on family, friends and those experiencing it?

These videos include people affected by the impact of drugs use and overdose who share some of their stories.

Australia’s Alcohol and Drug Foundation have a comprehensive site set up for IOAD. There’s helpful information here such as Signs and Symptoms of an Overdose, Harm Minimisation, How to Help in an Emergency, along with references and resources.

This morning on ABC Melbourne Jon Faine ran a great interview. The info’ paragraphs run as follows;

Cherie Short’s son Aaron died of a drug overdose in 2015. She tells Jon Faine we need to change drug policy and “make humane decisions” to stop others from dying.
“This tragedy is preventable, I believe overdose is preventable,” she said.

Ms Short is joined by Kayla Caccaviello, who dated Aaron and has overcome her own addiction to drugs to become a drug and alcohol counsellor.

The interview is titled “Humane drug policy could have saved my son”: Mum

You can download the 8 minute mp3 file here.

Activities for this year globally and across every state in Australia can be accessed on this page. Fortunately Australia is second from the top and easy to access. But of course please use the drop down menu for fast access to the area of your choice. Australia has 79 activities with 48 in Victoria, 11 in NSW, 7 in WA, 4 in QLD and TAS, 3 in NT and 2 in ACT.

Activities are varied ranging from O.D. prevention training, to art display, to group naloxone (opioid antidote) training, to afternoon tea – followed by naloxone training and a free kit, remembrance events to de-stigmatise overdose, etc.

Australia has only two supervised injecting centres. One, the MSIC in Kings Cross Sydney opened in May 2001 and after more than 11 years of successful trial moved to permanent basis. The MSIC in Richmond, Melbourne commenced on a trial basis at the beginning of 2018. Whilst it is running successfully and saving lives daily the entire concept is a punching bag for conservative politicians.

Regrettably whilst it is easy to manufacture the illusion of government funded drug induced harm and negative community appearances the peer reviewed evidence, globally, supports the health benefits of Safe Injecting Facilities. Always be aware of the myth of a Drug Free Australia.

This notion is pushed on the back of pseudoscience, the rejection of peer reviewed evidence and moral panic. You can read up on the antics of Drug Free Australia Ltd via their tag here.

Evidence backed themes that are often presented on IOAD support the fact that prohibition and the “war on drugs” waste money, ruin and cost lives. Harm minimisation practices such as harm reduction approaches like needle exchange and injecting facilities, prevent overdose, the spread of blood borne diseases and community dysfunction.

Evidence supports harm minimisation and particularly harm reduction.

Prescription Drug Overdose

One area to receive increasing attention again this year is that of prescription opioids. According to this ABC article OD fatalities have risen almost 40% in the last decade.

A constant concern for those who need adequate pain management via prescription, is that the “war on drugs” mentality may permeate policy modification under the belief it is a sensible solution. Once again the political conservative gravitates to this mode of moral dictation.

Overseas activity suggests that those who are denied prescription medication for prolonged pain management may find their way to illicit opioid abuse and inherit all the problems of crime, disease, socioeconomic stress and violence that come with such abuse.

We must yet again be careful that in managing this emerging problem we do not allow the denial of rights and an ignorance of incumbent facts such that we see punishment and manipulation of those in need.

Immunisation: Why we do it and how ‘herd immunity’ works

Denial of community immunity or herd immunity is a common feature of antivaccinationists.

In fact groups that spread harmful disinformation, such as the Australian based Australian Vaccination-risks Network (AVN), have for years been refining the denial of this evidence based fact. Notably they misrepresent what herd immunity is, primarily by referencing an aspect of herd immunity or an expected result of herd immunity.

The Australian Government Department of Health offer this definition;

If enough people in a community are immunised against an infectious disease, there is less of the disease in the community, which makes it harder for the disease to spread.

Immunisation protects both people who are vaccinated and also helps the entire community. It helps protect those who are too young to be vaccinated and those who can’t be vaccinated for medical reasons. This is known as community (herd) immunity.

Claiming that the “laws” of No Jab No Pay and No Jab No Play “are based on herd immunity”, Meryl Dorey of the AVN contends;

The theory claims that the unvaccinated are more likely to contract and transmit diseases than their vaccinated peers.

Travel to a largely unvaccinated country, get shots and you’re apparently in a protected bubble. Back home and they’d have us believe we need a 95 per cent plus vaccination rate to be protected and that a lone unvaccinated individual can be responsible for an epidemic.

Indeed rather than “claim” that unvaccinated community members will contract and transmit disease, herd immunity provides greater protection for the unvaccinated. Nonetheless herd immunity cannot protect any particular unvaccinated individual and is very important with respect to protection from measles infection.

This is why individuals who cannot be vaccinated for specific reasons or those with weakened immune systems will be better protected in a community that has a vaccination level of 95% or above. In certain communities where vaccination levels are low, herd immunity and the cluster of immune individuals doesn’t exist. In this instance measles can easily spread from an infected individual to unvaccinated individuals.

If not for herd immunity providing protection to those who refuse vaccination and deny their children the protection of vaccine induced immunity, many of the false beliefs held by antivaccinationists could not persist. The success of so-called natural remedies, homeoprophylaxis and so on persist simply due to the protection of herd immunity.

  • The video below was produced by the BBC and provides an accurate summary of vaccination and herd immunity.

Immunisation: Why we do it and how ‘herd immunity’ works – © BBC News

Discredited anti-vaccine conspiracy theorist Judy Wilyman has even used denial of herd immunity in her ongoing attacks on Australia’s successful vaccination policy. Wilyman wrongly contends that only public health reforms such as sanitation led to the control of vaccine preventable diseases.

Vaccines did not create herd immunity to control infectious diseases, is an open letter on her website. The monumental flaw in her fallacious claim begins with her use of only mortality, and no morbidity data.

Also, Wilyman refers to changes in public health occurring before 1950. This ignores more modern vaccines such as that for Haemophilus influenzae type b (Hib) used in Australia from 1993 and later in Kenya from 1999.

Only vaccination can explain the control of Hib and the emerging success of the HPV vaccine.

Black Salve – The Pro-Necrotic Agent

Last April Questions for Pseudoscience published an informative video on the very nasty, dangerous, bogus skin cancer “treatment” known generally as Black Salve.

Main points might be summed up as;

  • It isn’t anti-tumour cream.
  • It is anti-skin cream.
  • It kills tissue via the caustic salt zinc chloride (listed by the FDA as a fake skin cancer treatment) and sanguinarine (a toxic alkaloid).
  • The combination of zinc chloride and sanguinarine is “incredibly lethal to living tissue”.
  • Apart from burning skin due to its caustic nature zinc chloride adversely effects other body organs and systems (eyes, G.I. tract, lungs).
  • Sanguinarine blocks sodium potassium pumps located in the cell membrane, killing cells.
  • The ridiculous myth peddled by proponents of Black Salve is that cell death can be controlled by removing the salve at just the right time so that only cancer cells are effected.
  • However once begun the process continues leading to widespread necrosis. As cells die, enzymes are released leading to the breakdown of neighbouring cell membranes.
  • A domino effect follows leading to widespread cell death.
  • Thus Black Salve is really a Pro-Necrotic Agent and will kill any tissue it comes into contact with.

In March 2012 we visited the issue of AVN selling the One Answer To Cancer DVD – a blatantly bogus promotion of Black Salve. The post included the banning of this dangerous product by Australia’s TGA, (Therapeutic Goods Administration).

The TGA at that time issued a warning on Black Salve, which was covered by the ABC’s The World Today.

  • Listen to the audio in the player below;

-———

————————————-

Fake news and the spreading of measles

“Fake news” isn’t my favourite term for the disinformation spread by antivaccinationists. However it conveys a meaning that is usefully accurate when it comes to labelling deception spread with the aim of misrepresenting the facts about vaccines.

The narrator in the US video below asks the question, “Is fake news making people sick?”. He notes that the country has broken a 25 year old record for measles cases this year. At the time of making the video there were over 700 cases across 22 states since the beginning of 2019. In states where population density is high we can expect to see the impact of vaccine induced immunity and herd immunity (or the lack thereof) in their unmistakably predictable manner.

New York city has had over 400 cases since October 2018. Some – not all – members of the orthodox Hasidic Jewish community have been avoiding vaccines. The narrator tells us this is due to “rampant misinformation around vaccines”, even though the orthodox community “overwhelmingly” believes in vaccines. One woman seems to doubt vaccine safety and efficacy. She argues that “some people question why would I subject my three year old to toxins when it’s not going to protect him or her”.

There is an increase in insular socialising habits in close orthodox communities. This ensures the successful spread of misinformation by The Vaccine Safety Handbook. Packed with the most well constructed vaccine myths, it targets these communities with well debunked anti-vaccine conspiracies, codswallop and even commentary from rabbis, specific to Jewish religious law.

WhatsApp groups have been set up to push anti-vaccine disinformation further, with some orthodox members reporting that their only source of news is via WhatsApp.

If this reminds you of the Somali community in Minnesota in 2017 and 2011, you’re not alone. 80% of reported measles cases in 2017 were of Somali children whose parents had been convinced of the risk between autism and MMR. It was the largest measles outbreak for 30 years.

What’s this got to do with orthodox Jews in New York? Well I mentioned the insular nature of close communities. In an article headed Minnesota’s measles outbreak is what happens when anti-vaxxers target immigrants, it is noted some of these Somali Americans had concerns about higher than average rates of autism amongst their children. This entire episode is indicative of the impact that calculated disinformation can have. Particularly when provided in an area of uncertainty and despite the effort and funding from health experts and government authorities.

In 2008 Somali parents stressed that there appeared to be more 3-4 year old Minnesota Somali children enrolled in the public preschool special education program for Autism Spectrum Disorder, compared to the overall percentage of Somali children enrolled in public schools [page 4].

Also a couple of years before this time MMR vaccine coverage had started to decrease in Minnesota-born Somali children from 2006 at which time rates had been above 90% [Figure 2].

Cultural differences meant that the most genuine efforts to assist the Somali-American community with this issue proved difficult. There is no word in Somali for “autism”. Indeed there is no grey area as one Somali parent put it. Mental health is seen as either “crazy” or “sane”, and this leads to the fear that a child may be called an unhelpful name within the community. A name used behind the parents’ back [page 4].

The Minnesota Department of Health (MDH) worked to re-examine enrollment data for pre-school aged children in the special education program. The results were published in a report which tended to focus on participation rates only. The report [pp 4-5];

…did not attempt to measure the true occurrence of ASD in all children, and it did not attempt to identify possible causes or risk factors for ASD. Instead, the focus was on developing a better understanding of reported differences in program participation rates among preschool-aged children enrolled in this MPS program.

The three main findings in the report confirmed parent’s observations and also raised questions as to better outreach services to Somali children vs genuinely higher levels of ASD, compared to non-Somali children accessing ASD services outside of the MPS. The proportion of Asian and Native American children participating in ASD programs was significantly lower. The cause for this remained elusive. Participation rate differences between Somali pre-school children and pre-school children from other ethnic backgrounds decreased “substantially” over the three years studied. The basis for this final point remained unclear.

Following the 2009 MDH report advocates for the Somali community called for further research. The CDC, NIH and Autism Speaks provided technical assistance and funding to the University of Minnesota. The aim was to focus on ASD in Minnesota and within Somali vs non-Somali communities. The MDH and the University of Minnesota’s Institute on Community Integration added in-kind staff and funding.

Still, we need to remember that it was 2008 when Somali parents first raised their concerns about ASD with the Minnesota Department of Health.

Enter disgraced fraud, data falsifier and ex-gastroenterologist, Andrew Wakefield, who was struck off the U.K.’s General Medical Council 21 years ago and the many-faced Organic Consumers Association. Wakefield targetted and set about convincing Minnesota’s Somali Community that MMR could not be trusted as health authorities claimed. It caused autism he lied. The rumour spread through the community. During the 2017 measles outbreak Wakefield insisted he didn’t feel responsible at all.

In short Wakefield and fellow antivaccinationists spread his anti-vaccine lies with the result that MMR vaccination fell in the Somali community for a number of years. Immigration status can be a risk factor with respect to immunisation status and this fact played very well into the hands of antivaccinationists.

Nonetheless, no vaccines cause autism.

It’s important to remember, and realise, how much damage antivaccinationists can do to public health. Yes, “fake news” is making people sick. Cities with high density and insular communities that are convinced to skip vaccination will constantly face the possibility of outbreaks. The anti-vaccine lobby and their minions will continue to spread misinformation and where possible it must be refuted.

I read a comment recently dismissing the need for any vaccine and contending that only three people had died since 2000. Forgetting that this US citizen is ignoring the rest of the world, it is just such complacency that helps drive the luxurious nonsense that vaccines are more harmful than the diseases they prevent.

Because after all, in the developed world vaccines are a victim of their own success.