Drug War tactics driving up HIV/AIDS

The Global Commission on Drug Policy recently released yet another report condemning illicit drug prohibition and the War on Drugs.

Entitled The War on Drugs and HIV/AIDS – how the criminalisation of drug use fuels the global pandemic the report lists 6 key dynamics behind the trend.

1.) Fear of arrest drives persons who use drugs underground, away from HIV testing and HIV prevention services and into high risk environments. 2.) Restrictions on provision of sterile syringes to drug users result in increased syringe sharing. 3.) Prohibitions or restrictions on opioid substitution therapy or other evidence based treatment result in untreated addiction and avoidable HIV risk behaviour. 4.) Conditions and lack of HIV prevention measures in prison lead to HIV outbreaks in incarcerated drug users. 5.) Disruptions of HIV antiretroviral therapy result in elevated HIV viral load and subsequent HIV transmission and increased antiretroviral resistance. 6.) Limited public funds are wasted on harmful and ineffective drug law enforcement efforts instead of being invested in proven HIV prevention strategies.

Let’s forget “drug war” and call this problem what it is. Treating drug use as a criminal offence. Now, just by raising that image we’re into different waters entirely. Pointing to problems with the criminal model immediately evokes suspicion of compulsory promotion of illicit drug use. We’re conditioned to assume if we don’t punish drug use, it will be everywhere and bring about a host of nasty outcomes.

Mostly, we’re well conditioned to associate drug use with crime and to see it as criminal. Stitched on to this is the pop culture image from which we draw stereotypes. My favourite is one I often refer to as Quinn Martin. Quinn Martin Productions brought us Streets Of San Francisco and a host of other unrealistic 1970’s TV Cop shows. If you wanted a crime – it was drug related. A bad guy or a weak willed loser? Toss in a druggie.

Of course, I’m not suggesting we imagine this. The reality is criminals are made from associating in criminal circles and from being incarcerated, regardless of the reason. How this fits in with the drug-crime punishment model was addressed recently by eminent Australians who authored the Australia 21 Report. They state:

The prohibition of illicit drugs is killing and criminalising our children, and we are all letting it happen

Rather than legalisation alone, that report discussed regulation, decriminalisation and de-penalisation. Far from being an open slather free ride these measures involve control, certain losses of freedom, the need to demonstrate responsibility and a major focus on rehabilitation back to a productive and useful lifestyle. What they don’t involve is the destruction of lives and sustaining criminal enterprise at huge cost to the community.

Yet in Australia we do very well managing HIV/AIDS in injection drug users [IDU]. 16 million use IV drugs globally. Almost 20% live with HIV. Fortunately, Australia managed to keep that level at 3%, and a significant number of that sample were at higher risk statistically from acquiring HIV from another high risk behaviour. This level remained stable for decades.

So the question does arise. Apart from acknowledging shocking human rights abuses, tragedy in many nations and an ongoing source of disease and corruption, what policy aspects need we mull over?

Since the Howard years Tough On Drugs initiative and emergence of groups like Drug Free Australia lobbying against expanded protective measures, the level of HIV in IDU jumped to 4%. It remains an exquisite example of how just a few years of delayed and abandoned Harm Reduction responses, increased punishment and disinformation about Harm Reduction efficacy has an immediately devastating impact on HIV control in Aussie IDU.

The fact that this collective undermining of Harm Minimisation occurred during a period when Harm Reduction services, research and supporting evidence expanded rapidly in Australia is testimony to how effective disinformation and intuitively themed attacks on evidence can actually be.

Still, as of April this year we remain extremely fortunate thanks to Harm Reduction:
HIV in IV Drug Users matched to Harm Reduction

The single greatest sabotage of Harm Reduction initiatives under the auspices of John Howard, was the suppression of a heroin on prescription trial in 1997. This had strong bipartisan support and the Federal Health Minister, four States and the ACT were excited about the decision to go ahead. Under instructions from then ANCD head Major Brian Watters – later to become a Board member of Drug Free Australia – Howard immediately vetoed the decision.

Exactly how many HIV cases, ruined lives and deaths this led to is impossible to estimate, and I would err toward a minimal estimate. Still, 15 years later we can assume the body pile is now somewhat impressive. In what is unique insight into how Howard in turn manipulated the zealots who tried to manipulate him, he never flinched on needle exchange.

To his credit he continued to fund over a thousand outlets across Australia, with some specialising in bulk dispensing, others in hard core risk management. Abandoning these programmes was insanity, despite conservative lobbyists being convinced he might do so. Yet to Howard, being seen to usher in heroin prescription – “free heroin” – as shock jocks called it was political suicide.

Despite strong support for our official policy of Harm Minimisation, which accommodated extreme spending against smuggling (Supply Reduction), this is how he presented his thoughts in 1998:

The policy of zero tolerance of drug taking in this country is a wholly credible policy and policy that ought to be pursued more vigorously by government and by people who are concerned about the problem.

Of all the lies he told, this remains one of my favourites. There was no such policy beyond words. He seemed to despise everyone equally. Which was essential for the politician he became. All that mattered to Howard was Howard, and securing votes. Manipulating drug workers, users, science advisers, policy experts and voters over what was a social crisis at the time was pure business.

British Columbia did introduce heroin on prescription in 2005. 5 years later the effects of the combined measures on HIV were compelling:
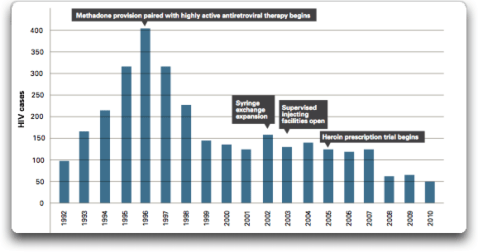
British Columbia: HIV infection matched to Harm Reduction initiatives

Similar success from heroin on prescription is found in every nation to usher in trials and programmes. Sadly, Australia was ready before the Howard years. We were in fact, world leaders. Now it’s a different story. We have one Medically Supervised Injecting Facility that ran as a successful trial for 11 years.

Seven of those 11 years were due to disinformation and sabotage from conservatives. In October 2010 the Kenaelly NSW State government passed a Drug Misuse and Trafficking Amendment bill to ensure the Centre became permanent. 11 years of moral panic was, at least legislatively, silenced.

Whilst actually attacking Harm Reduction initiatives, confusing methadone and buprenorphine with illicit drugs and muddling the lot in with AFL drug policy, Alan Jones delighted us with his wisdom on “Harm Minimisation”, in mid 2007 [MP3 here]. Obnoxious, offensive and completely ignorant of facts it is also somewhat representative of Aussie views today:

So today Australia has a long, long way to go before we do, if ever, fully recover from the rise of anti-drug conservatives under John Howard. They did far more damage than just raise HIV infection by 1% in injection drug users. Our fluency with progressive policy and public maturity has been undermined. Australia waits, on pause.

33 million people live with HIV today. Outside sub-Sahran Africa IV drug use accounts for 1/3 of new infections. For almost 15 years annual HIV infections have been falling on a global scale. Except for seven countries wherein HIV infections increased by about 25% primarily due to IV drug use.

The “drug war” is full on in Eastern Europe and Central Asia and unsurprisingly 5 of these 7 countries are in these boundaries. In the last decade people living with HIV in these areas has close to tripled. Russia has resisted Harm Reduction measures keeping methadone illegal and charging users for needle possession. As this demographic is actively abused by law enforcers the motivation to use needles based on access convenience and minimal time is heightened. The results are clear:

HIV infections – Russian Federation

Thailand has impressively cut HIV infection in workers in the famous tourist attracting sex industry from 40% in the mid 1990’s to around 5% today. This pulled male clientele infection rates down in parallel. At the same time fierce drug war tactics led to 2,500 “death squad” murders in 2003 and HIV is up to 1 in 2 IDU in some regions. A comparison of different demographics for HIV infection is compelling:
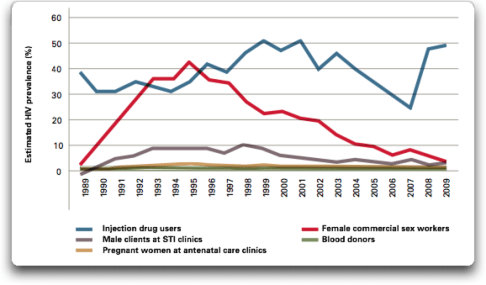
THAILAND: HIV infections per demographic

In a splendid example of stupidity the USA reinstated it’s 21 year ban on federal funding for needle exchange programmes only 2 years after ending it. A stark lesson for Australia, constantly under the assault of disinformation from anti-drug group Drug Free Australia, can be found on page 9 of the GCDP Report.

Recently in reviewing the history of Harm Reduction and HIV, I noted the stark difference between not just nations, but regions within nations favouring HR as a powerful controller of HIV spread. Similarly today it can be seen that in nations with extreme law enforcement, and regions within the USA with the most intense law enforcement that HIV levels are higher than those with low law enforcement.

For instance, a study of the 96 largest US metropolitan areas found that measures of anti-drug “legal repressiveness” were associated with higher HIV prevalence among injectors and concluded: “This may be because fear of arrest and/or punishment leads drug injectors to avoid using syringe exchanges, or to inject hurriedly or to inject in shooting galleries or other multiperson injection settings to escape detection.”

DFA fallaciously – and skillfully – report the exact opposite. Similarly DFA urge for dedicated Harm Prevention measures, described already on this blog as crude behaviour modification. Whether through blind or biblical force the aim is to do just that: force drug users to stop by changing behaviour. Forget the addiction and crush the symptom.

The easiest way to do this is control the environment. Enter compulsory detention. What DFA have called “compassionate detention”. The models they are considering are terrifying. Not only is HIV infection spread through these centres, they fail to offer any addiction treatment. Forced abstinence is associated with high fatality relapse.

Once infected with HIV criminal and punitive approaches act as a disincentive to testing and treatment. Requirements to be drug-free in order to receive treatment (as in Sweden) and denial of certain rights like child custody and employment correlate directly to higher HIV/AIDS fatalities. Confidentiality breaches and stigma impact frequently due to law enforcement regardless of country.

This leads to higher circulation of HIV in the community as treatment has been shown to reduce HIV transmitted via blood and body fluids. As such it is vital all demographics in all communities can be reached through treatment which ultimately leads to prevention.

Incarceration also increases HIV infection and Australia is heading toward a USA type model which has 25% of prisoners listed as HIV positive. Fortunately our initial lower levels in the IDU population will protect us significantly from such a nightmare. Unusually, prison needle exchange is resisted strongly. DFA play the key lobby role nationally and prison guard unions seem intent to deny evidence in favour of their health.

Australian prison guards profit enormously from selling syringes to prisoners. Secondary to money is the control of prison dynamics, control of prisoner behaviour and the essential control of these transactions in corruption entire. A syringe is power in the prison setting. The sooner we remove this tool from guards and protect prisoner health with clean exchanges, the better.

Resources spent on law enforcement are resources not spent on health initiatives generally, on a global scale. With drug crime and infection encouraged by the former and lessened by the latter, it is clear we face a major global challenge. Public health is the first principle of drug control.

Settings where HIV prevention measures have been curtailed as a result of economic concerns have been particularly vulnerable to increases in HIV risk among injection drug users. For instance, a greater than 10-fold increase in newly diagnosed HIV infections among injecting drug users has recently been reported from Greece during the first seven months of 2011.

Australia remains incredibly lucky and indeed most fortunate in this global picture. What cannot be ignored and what must be cautioned against is our slow morphing into a landing pad for USA styled conservative disasters. DFA is an arm of Drug Free America Foundation and act at their bidding. DFAF have their “division”, the Institute on Global Drug Policy who fund the Journal of Global Drug Policy and Practice.

This is no journal but a vehicle for lobbying against progressive drug policy primarily that which targets HIV control. All get together and play at the Swedish based World Federation Against Drugs which similarly is nothing like a “world federation”. What they strive for is patently out of this world.

As today’s most brilliant minds accept the evidence condemning prohibition, the global Drug Free Whomever groups seek to defend the UN Drug Conventions that originated in 1961.

Fortunate we may be, but complacent we cannot afford to become.

Dumb and Dumber: Making antivaxxers look good

Sometimes what may seem like a good idea can backfire horribly because well, it really wasn’t much of an idea at all.

So it was with a post headed Australian Vaccination Network Seminars on the irreverent and uniquely themed blog, JABS, Loonies – Justice, Awareness, Basic Support and Mind Blowing Stupidity. Keep that last bit in mind – mind blowing stupidity.

Now, I get this blog. No problem. It’s giving voice to no-nonsense criticism using colourful language. The author, Rebecca Fisher or just Becky, set out to post a daily comment from JABS to reflect the tenuous grip on reality we see accompanying top shelf antivaccination beliefs. Then, to Becky’s horror JABS seemed to moderate the “loonies”. Enter Age of Autism and The Australian Vaccination Network. An excellent choice, I concur.

Becky sprinkled the above post with plenty of swearing and foul ridicule. If you know how Becky writes and appreciate her style, it may well be quite funny. I personally enjoyed the description of Greg Beattie’s book. Not that I’d describe it that way, but because Beattie is a smug, attention seeking liar happy to profit from the harm he inflicts on other Aussies. His book is banally deceptive dreck, the title of which is not worth repeating.

So, “used bog roll” does suffice although I would query the ultimate value of additional swearing. After all, describing the real Greg Beattie is far more shocking, sickening, disgusting and of course hilariously funny, than any colourful delivery could hope to accomplish.

Like the other person Becky ridicules, Meryl Dorey, he denies the origin of HIV/AIDS in favour of the notion it’s a vaccine wot dunnit. When Dorey’s “invitation” to genuine medical practitioners to present at these “seminars” was knocked back, Beattie “volunteered” to take the place of high caliber professionals. Managing in the same offer to personally sneer at another doctor. In accepting this mockery, Dorey cut her potential attendance figures significantly.

Jane Hansen admirably describes the Greg we all know and love in action at Lismore:

In the absence of a balanced debate, anti-vaccination author Greg Beattie says he is going to try to convince everyone that vaccinations are great. He confesses he did a 15-minute Google search on the benefits. “We see these recurring themes ‘vaccines saves lives, medical miracles, diseases used to kill children’,” he says, but his tone is dripping in irony. […]

He’s done a lousy job of explaining the benefits of immunisation. We did not hear, for example, that diphtheria – the biggest killer of Australians in the early 1900s – has virtually vanished. Or that the 150 deaths in Australia in 1963-64 became zero by 1998, or that the only recorded death recently was that of young woman from Queensland who was not immunised as a child. Her immunised boyfriend carried the disease back from an overseas trip. She died, at 20.

It’s plain from the petulant lead up and the reality described by Hansen that all Dorey’s propaganda on pro choice and respect for medical advice – she called one aspect “a crock” – was forgotten for what is essentially deceit. No doubt Becky is well aware of this, and in her unique way summed up Dorey’s sociopathic and narcissistic personality disorders by labelling her f***ing evil.

What Becky might not realise is that Dorey and her minions live for this very type of insult. In fact, whilst writing “in character” if I may employ a phrase, it’s easy to “hear” the tone in which it’s intended to come across. It may resonate like Penn and Teller. Or well known stand up comedians who leave us doubled over in tears, merely capable of nodding in agreement.

But the gamble is, will your audience always appreciate it? Well no, and I’m sure Becky is not that gullible nor rightly gives a toss for prudish criticism.

The problem we arrive at however is that Dorey will use this “attack”, as her personal academic-in-waiting documents such criticism, to garner sympathy with the very people Becky was hoping to persuade against tolerating such seminars. The bigger problem is that it’s a kick in the guts to those who have been tackling the AVN for years. Whilst it’s true antivaxxers use a similar template, AVN in-group management is a strictly coordinated affair.

Recently the AVN has been caught with little more than false tales of persecution. Turn up the brightness on this mess and it can be seen that their manufactured dissent is truly ridiculous, whilst a quick tally of vile outbursts, scams, intimidation and bullying puts the AVN in a league of it’s own. For the first time in two years, Dorey has not invented stories of being hassled and threatened by “the skeptics” prior to her seminars.

Well, now she doesn’t have to. The reaction to Becky’s post was swift. Cunning from the outset, notice Dorey doesn’t (or can’t) refer to herself. She claims the post is “attacking someone who believes in informed vaccination choice…”. No. It attacks only Dorey and Beattie. But almost exclusively Dorey. There’s some weird depersonalisation issues at play in that troubled, dangerous psyche.

Someone has just sent me a link to this blog Dorey announced on Facebook. And:

 – which is the foulest, most vile piece of rubbish I’ve yet to read from the pseudo-sceptics. This blog is written by a person who can’t seem to write a sentence without both attacking someone who believes in informed vaccination choice and calling them a 4-letter word.

Great. “Pseudo-sceptics” is Dorey-code for actual skeptics, science advocates and devotees of scientific skepticism. In using the term Dorey makes a mockery of herself because the definition encompasses AIDS denial, vaccine denial, indeed evidence denial in general:

Pseudoskepticism, by contrast, involves “negative hypotheses” – theoretical assertions that some belief, theory, or claim is factually wrong – without satisfying the burden of proof that such negative theoretical assertions would require.

RationalWiki take it further such that one almost expects to read Meryl Dorey’s name as a famous pseudoskeptic. In effect, Dorey has confused notions from Hume’s philosophy of True Skepticism with a Facebook post an antivaxxer made one day using the term. Dorey delightfully called it “a keeper”, and along with her inability to research the rest is history.

Yet, as incredibly wrong as she is, her response to Becky’s post indicates a shift toward blaming her regular critics for being vile and foul mouthed attackers. Horribly she gets a free kick for that appallingly misleading “informed vaccination choice”, to describe the lockstep of vaccine conspiracy.

For impact Dorey copied in Becky’s list of top search results, then continues:

Notice the addition of “small hate group”. Suddenly Becky is a hate group? No. Dorey may follow this up with a letter blaming Stop The AVN and The Australian Skeptics. Directly pointing the finger for suppression of free speech, threats and footnoted with Dr. Brian Martin’s “research”. It’s vintage Dorey, twisting anything to her advantage and tutoring her minions to the nth degree.

Suddenly she’s gone all patriotic. One day Australia is a Health Fascist Scientocracy. Next we have our American loiterer, hell bent on destroying Australian public health, actually telling Aussies what the RSL stand for. Incapable of independent thought the flying monkeys screech into action:

Until then, Dorey hadn’t been urging her minions to write to the RSL or other Services clubs. Perhaps however, other diligent health advocates were in touch with various venues. Perhaps directing them to various accounts of Dorey’s first effort and her vicious ranting screeds in response to criticism.

Now these same clubs or individuals will read the far more offensive and pointless attack against Dorey, and associate every cautionary warning with that outburst. Those making the decision are unlikely to know the first thing about antivaccination deceit. They are far more likely to be the type of prudish critic Becky would not attract to her blog initially.

Dorey will win the sympathy vote and the persecution meme is off and running again.

The flapping, swooping and screeching actually gets worse. In this thread is a “Chris Savage” who earlier lied heroically:

I am an ex-Sgt of Police after 20 years in Queensland. Every SIDS mother told me their babies were healthy prior to vaccines and then deteriorated and died after.

So Dorey’s Darlings – and particularly stalker, poor Liz Hempel – are grabbing screenshots. Hempel has stalked one woman who jokingly said she’d throw fruit, found out she is a police communications officer from her blogger profile and urged for a complaint. Sergeant SIDS likes the idea and has chimed in with the details on where to lodge a complaint.

Now, I think that’s as pathetic as everyone else does. On a positive note it helps my steadily increasing dossier on how AVN members are demonstrably attacking people well outside of any “debate” that Dr. Brian Martin purports to be documenting.

I’ll spare you any more of the thread. It’s full of fawning and worship. At one point Meryl is likened to a giraffe and Becky’s post to a skinny, malnourished, barking chihuahua.

Whilst Meryl’s head is certainly in the clouds the problem with Becky’s post is not the suggestion to forewarn venues and certainly not the points listed. Meryl is indeed a liar, thief, scam artist, criminal and so disturbed on so many levels she appears to not care if children live or die or are brain damaged for life.

All these points can be made on merit. Not with abuse. Abuse only feeds into Meryl’s diversionary tactics and tend to lend credence to her schemes by lowering the tone of her opposition. Dorey has no evidence and that is plain. All evidence on vaccination shows her to be dangerous and all evidence on herself bears out what I just described above.

Now however, a very good opportunity to at the very least have her scrutinised at these venues has either been lost or markedly tainted. The tiresome and scratched record of persecution and abuse gets a new lease of life. Every audience will now hear of this “most vile piece of rubbish”. Every attendee will be told this is how all of her critics behave.

Personally I have no problem with Becky’s post. I think it’s entirely proper to place irrational enemies of reason in their proper place. That does include ridicule and free speech makes that everyone’s prerogative. What I am concerned about is the outcome, which was entirely predictable.

So what’s been achieved? Nothing. Backward steps. Unless one has personal contacts within the RSL it would be damaging to now write to them. Letters critical of Dorey will be associated with a senseless foul mouthed rant. The “loonies” Becky wants to launch into have a new lease on life and have bonded splendidly, reinforcing their beliefs. That is exactly what we don’t want.

There’s no doubt that abusing someone over their beliefs reinforces those beliefs. This holds true for onlookers and is actually helping Dorey. That’s bad for upcoming generations. It’s also true Dorey exploits abuse and criticism by injecting it with a dose of fiction. I doubt she’s finished with this one yet.

Doing the right thing for people that the Dorey’s of this world have abused – many of them now “loonies” themselves – doesn’t require mockery and ridicule. Garnering support and protecting children and future generations from the damage these creatures do is something that can, if not must be done on merit. Meryl Dorey might be cowardly, cruel and callous, but she still knows how to score points.

That’s no joke.

Hepatitis B Vaccination: A Chinese Success Story

The vaccination effort against Hepatitis B, especially to protect newborns, will not stop

– Dr Yang Wei Zhong, Deputy Director General of the China CDC –

Australians are unfamiliar with the impact of large scale infection from Hepatitis B virus [HBV].

Ways of controlling the spread of infection include vaccination of health care workers against HBV, that infection with HBV is a notifiable disease, the quarantine of patients suspected of having HBV, ongoing quarantine procedures for patients diagnosed with HBV, extensive education and follow up of patients upon discharge and Harm Reduction initiatives.

So successful have these measures been that many Aussies erroneously believe HBV is exclusively a problem for high risk demographics such as IV drug users or sex workers. This misconception itself is as dangerous as high risk behaviour because it leads to the belief that protection from infection is linked to how one identifies oneself.

Indeed, IV drug users and sex workers are often highly educated about the risk of HBV infection and implement safe injecting and safe sex practices. Many seek out or are offered the HBV vaccine by their own or any GP. The fact is everyone is susceptible to infection with HBV or any blood borne virus.

Tragically the antivaccination lobby has done much to mislead some Aussies into what could almost be termed lethal complacency. By both dehumanising high risk demographics and falsely linking the HBV vaccine to injury and death, they have propagated ignorance and fear, condemning many to premature death from liver failure. In some cases the virus will be cleared over time, but there is no way to manufacture this outcome.

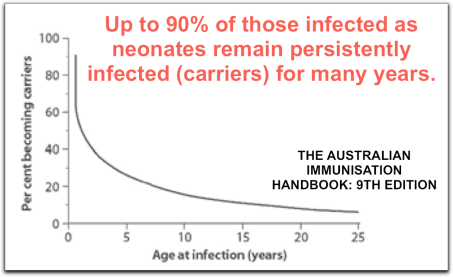
HBV positive individuals who would not exist but for antivaccination propaganda, can transmit the virus for many years post infection, completely free of symptoms.

The WHO observe:

HBV may be the cause of up to 80% of all cases of hepatocellular carcinoma (liver cancer) worldwide, second only to tobacco among known human carcinogens. […]

One should not judge by appearance: most infected people look perfectly healthy and have no symptoms of disease, yet may be highly infectious.

As Australia’s population changes rapidly through immigration and we travel more readily our risk of HBV infection steadily increases. At no time in our history has vaccination against HBV been more important. This will be true tomorrow, next week, next year and next decade. For this reason HBV vaccination is available to newborns.

It’s safe to say that everyday in Australia new lives not only begin, but are in many cases saved and protected from infection through this initiative. In the USA at least eight people per day die from HBV related complications. 25% of carriers world wide – over one million people – die each year from chronic hepatic insufficiency, cirrhosis and liver cancer brought on by HBV infection.

The protective effect of vaccination rolls on for newborns, toddlers and children. Children not born to a HBV positive mother are still protected from the many modes of infection as they grow and go about their lives. There are more concerns than sexual behaviour or the sterility of drug administration. Blood borne is invisible. Only a tiny scratch or cut to the skin or oral mucosa is enough to allow the HBV virus to infect.

It can remain viable for up to a week in blood stains on razor blades, nail clippers, nail files, table tops and can be transferred to a tiny wound by moistening dried, viable blood stains on bedding. We can extrapolate from that to see potential risk comes from any sharp surface or object or textile that children play with and chew on.

It would appear that if complacency was to be justified it is in the parents whose children are vaccinated at birth.

Fortunately antivaccination lobbying and planned fear mongering is not the global norm. At the same time we can celebrate the truly life changing roll out of Hepatitis B vaccination in China.

In 2004 The Association for Asia Research reported 690 million people in China were infected with HBV:

According to the Xinhua News Agency, April 25 is Children’s Immunization Day in China. China’s health department has named this day with the theme of “vaccination prevents hepatitis B” this year. They want to draw the public’s attention to the importance of vaccinating children for hepatitis B vaccination to stop further spread of the disease in China.

A recent study showed that about 2 billion people in the world are infected with hepatitis B; 690 million of them live in China. The chronic hepatitis B carriers in China number about 20 million. An average of 280,000 deaths annually are caused by hepatitis B and related liver diseases.

Still today in China HBV infection carries stigma much like HIV which, in what should be a wake up to Australian and USA antivaccination mobs, prevents middle and upper class individuals from seeking blood tests. Despite HIV awareness being much greater, as recently as 2007 the HIV to HBV infection ratio in China was 1 to 200.

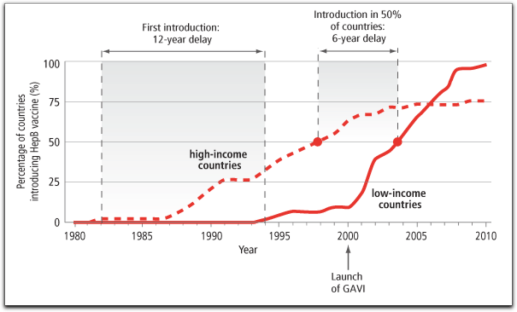
In 2005 the GAVI Alliance began to work with Chinese officials in combating HBV through the vaccination of newborns. GAVI had already made significant inroads in developing nations. In 2004, 22 years after HBV vaccination was introduced to Italy, 50% of low income nations had included the vaccine in immunisation schedules.

What’s truly impressive about GAVI’s impact, is that this was only six years after the 50% mark was reached for high income countries. Over 75% of that catch up followed the launch of GAVI.

In 2001 10% of China’s population were chronic carriers of HBV, which was responsible for hundreds of thousands of deaths from cirrhosis and liver cancer annually. In 2004 this was estimated to be 280,000 deaths. Less than 40% of children in poor areas were being immunised.

In 2002 the Chinese Centre for Disease Control, the Chinese Government and GAVI formed a partnership to co-fund HBV vaccines. This lasted until the end of 2010 and produced a concerted effort to fight infection. Over 25 million newborns in remote and poor regions of western and central China were given free HBV vaccines.

As many women traditionally gave birth at home, raising awareness as to the value of immunisation and encouraging mothers to give birth in hospital became a crucial part of the programme.

In 2005 the Chinese government added HBV vaccines to the national immunisation schedule. At the beginning of the project 64% of children were immunised with the first dose at birth. Now this level is over 90% in the majority of these remote regions. Today, less than 1% of children aged under 5 are carriers of HBV.

Dr Mark Kane, a GAVI Alliance founding Board member states:

The success of the introduction of hepatitis B vaccine is a model, showing us what we need to do and what can happen as we embark on efforts to introduce important new vaccines against pneumonia, diarrhoea and cervical cancer.

China remains a country where vaccines are not a victim of their success. 25 million newborns have been given a start in life that many of their parents could only dream of. Australia’s most vocal antivaccination identity claims Chinese herbal medicine has been shown “to clear Hep B from the system… there are peer reviewed studies on this”.

It appears the Chinese themselves would, and can, disagree without saying a word. There is no cure. The virus can and does clear of it’s own accord in some cases, which might easily be the subject of poorly controlled studies.

However the ravages of Hepatitis B infection in China is a matter of recorded history. I wish them all the best for the future.

Because after all as we can see yet again, vaccination saves lives.

Advanced Medical Institute: The “unconscionable conduct” continues

In a nation awash with health scams that pitch themselves as natural alternatives to medicine, it’s less common to find scams that position themselves as “medical”.

Even further apart are the medical tricks that prey upon vulnerable members of the public, such as Dr. Death Sartori. Or those that position themselves in a predatory manner, ready to strike when average Aussies suddenly find themselves vulnerable and in unfamiliar territory.

This definition easily applies to the one third of Aussie men aged over 50 who deal with sexual dysfunction or erectile dysfunction every year.

Enter Advanced Medical Institute whose defence against The Australian Competition and Consumer Commission for “false and misleading” conduct goes back at least to 2003. The man behind the scam is Soviet Era trained doctor, Ukrainian Jack Vaisman, unregistered in Australia. He apparently also earned a PhD from the USA which enables his title as “Doctor” to get a misleading airing.

Another company he earlier owned, On Clinic led Professor David Handelsman head of andrology at Concord Hospital’s ANZAC Research Institute to remark under oath in 2009:

I’ve got to say, one of the most scarifying experiences as a medical practitioner I’ve had [was] seeing just how low quality this sort of medical care can be,” he said. ”It really shouldn’t occur in Australia in the 21st century … It goes back to a pre-thalidomide type of regulatory standards.

Professor Handelsman was referring to his mid 1990’s encounter with Vaisman. At that time Professor Handelsman was sitting on a Health Care Complaints Commission inquiry into On Clinic, called by the NSW Government. In 1996 the company pleaded guilty to charges of illegally importing individual constituents of Vaisman’s penile injection concoction. Each component was unregistered with the TGA, mixed in unregulated conditions then provided to patients with a syringe and instructions.

In March 2003 another company Vaisman (below) had acquired, Australian Momentum Health Pty Ltd, was convicted of supplying unregistered therapeutic goods. Even before AMI kicked off the last person Aussies needed dealing with male sexual dysfunction was Jack Vaisman.

Advanced Medical Institute gamble on blokes being too embarrassed to seek recompense for ineffective and outrageously priced off label use of dangerous or common and cheap medications. These are sold under long term contracts costing thousands of dollars in a practice described in 2009 as “pernicious, nasty and unethical”.

Of serious concern also is that erectile dysfunction may be an indicator of diabetes, kidney dysfunction, drug interaction, neuroses, neurological disorders, blood pressure irregularities or cardiovascular disease, prostate problems, penile conditions and other chronic conditions.

By hitting below the belt as it were with the famous “Longer Lasting Sex” advertisements, Vaisman was both targetting a symptom in older men and appealing to vanity or anxiety in younger men. A phone call was all it took.

Clearly, as the most cursory checkup – for example taking BP or physical examination – cannot take place over the phone, patient health wasn’t, and still isn’t part of the deal. This practice of “consulting”, diagnosing and prescribing medication ensuring locked in contracts over the phone at break neck, Gish Galloping speed, was the subject of a House of Representatives Standing Committee on Health and Ageing on August 25th, 2009. The litany of bogus science, cruel treatment and vile scheming is as extensive as the witnesses are impressive.

A lively exchange took place the next day between 2UE’s Mike Carlton, self appointed director of the deceptively named Australian Centre for Sexual Health, Richard Doyle and Jack Vaisman. An AMI shareholder Doyle (who also acted as Vaisman’s legal defence) is close to hilarious, suggesting everyone else is stupid for not keeping up with the latest science, including a remarkable study (not cited) showing that a phone call is superior to an actual consultation. Vaisman himself must be remembering a different inquiry.

You may grab the short MP3 here or listen below:

Ian Turpie admitted in 2006 he had lied about AMI “advanced technology” nasal spray. Vaisman had raged “Who gives a f**k?”, when AMI’s General Manager had asked if the advertisement was indeed a sham. The spray contains apomorphine, a drug used to treat Parkinson’s disease, and has been shown a dismal alternative to traditional solutions such as Viagra. AMI or it’s doctors did not advise clients of the superior alternatives.

Apomorphine is deemed ineffective by over 70% of doctors and it’s use for erectile dysfunction has been largely discontinued. In fact in cases that AMI would attract it is contraindicated. It’s mode of action works by increasing desire – not improving erectile function. In any case it is not worth thousands of dollars.

Vaisman was getting away with breaching TGA laws that render his spray a second-line therapy only if commercial alternatives are not available. Still, TGA impotency is hard to miss over the 20 or so years Vaisman has scammed Aussies. His “compounded products/prescriptions” came under TGA regulations that have exempted him from having to run any clinical trials.

Kelly Burke wrote in November 2009 following the report released by the Standing Committee on Health and Ageing:

By AMI’s figures, about 15 million nasal sprays, lozenges and sundry potions have been sold to the gullible and desperate over a decade. Yet not a single one has been subject to the administration’s quality control and safety requirements.

Vaisman has been permitted to exploit a regulation that allows doctors to prescribe individually tailored medications for patients for whom no alternative effective treatment is commercially available. […]

The vague wording of the National Policy for Technology-based Patient Consultations also needs to be tightened. […]

Close the Therapeutic Goods Administration loophole and tighten the telemedicine regulations as proposed in the report, and Australians will be able to wave goodbye to the screaming billboards, excruciating radio ads and tacky late-night television campaigns. And Jack Vaisman will be out of business.

By 2010 the Australian Competition and Consumer Commission (ACCC) had taken an new interest, raiding Vaisman’s offices in February. In December 2010 the same day the ACCC began legal proceedings against AMI, Vaisman placed the company into voluntary administration. The ACCC had launched proceedings against Vaisman, Advanced Medical Institute Pty Ltd, AMI Australia Holdings Pty Ltd, and two doctors.

On June 9th, 2011 The Brisbane Times reported:

The Australian Competition and Consumer Commission has started fresh proceedings in the Federal Court alleging that the company, famous for its billboards and radio advertisements promoting ”longer-lasting sex”, has failed to inform its customers that it is insolvent, and may not be able to provide medication for which some of them paid thousands of dollars.

AMI had continued trading since the time it went into voluntary administration. In a shifty move the business was sold to NRM Corporation Pty Ltd and NRM Trading Pty Ltd [collectively NRM], and very shortly after went into voluntary liquidation. NRM continues to conduct the AMI business.

The Australian Consumer Law (Schedule 2 of the Competition and Consumer Act 2010) had Unfair Contract Terms provision added in July 2010. This has allowed the ACCC to pursue a case against AMI for alleged unconscionable conduct. This is a significant move in consumer protection.

Nasty, deplorable, pernicious, predatory and coercive were the terms used during the House of Representatives Standing Committee inquiry into Vaisman’s conduct. His abuse of clients from 17 to 87 years of age is despicable. Unconscionable Conduct sounds about right.

The ACCC reported on it’s website last September that the Federal Court had granted orders to add NRM as respondents in the ACCC case against the AMI for unconscionable conduct and granted leave for the ACCC to pursue action “against the AMI companies in liquidation”:

The ACCC alleges that AMI engaged in unconscionable conduct in breach of the Trade Practices Act 1974 and NRM is engaging in or proposing to engage in unconscionable conduct in breach of the Competition and Consumer Act 2010.  The ACCC also alleges that Dr Lonergan was knowingly concerned in AMI’s conduct and Mr Vaisman being a former director of AMI and a current director of NRM was and is knowingly concerned in the conduct of those respondents.

The ACCC further alleges that NRM is in breach of the Australian Consumer Law by entering into long-term agreements for the treatment of male sexual dysfunction which contain unfair contract terms in relation to the termination of a contract.

Incredibly, so it came to pass. Under Vaisman’s shady direction NRM took “control” of AMI and continued to lure customers into unconscionable long term non efficacious rip off contracts with zero regard for consumer health.

You may have noticed the shift from Sniff and Stiff the piano playing penises on late night TV to the Genie who magically cranks up libido using a strip on the tongue. As noted by genuine experts in 2009, these advertisements are “destructive… a carefully constructed legal fiction.”

UPDATE: On April 22nd 2015 the ACCC reported that the Federal Court found Advanced Medical Institute had engaged in unconscionable conduct. The media release (MR 63/15) reads in part:

In his judgment, Justice North said “It is immoral to seek to harness the fears and anxieties of men suffering from ED [erectile dysfunction] or PE [premature ejaculation] for the purpose of selling medical treatments. To target the patient’s vulnerability in this way is to use an unfair tactic and that is a possible marker of unconscionable conduct”.

Justice North also stated “The technique of frightening men by telling them of the dire adverse consequences of not agreeing to treatment and assuring them that the treatment was effective was part of the business system of AMI and NRM. It was formulated by management and imparted in an organised fashion through scripts and training sessions.”

His Honour also found that NRM further breached the Australian Consumer Law by entering into long-term agreements for the treatment which contained unfair contract terms in relation to the termination of a contract.

The Court declared that the conduct of the respondents was unconscionable and made orders:

  • requiring that NRM compensate a number of the patients whose evidence was considered by the Court
  • permanently restraining NRM from:
    • making agreements with a patient or in respect of the supply of medications for the treatment of male sexual dysfunction unless the patient has a consultation with a qualified medical practitioner
    • making any statement about the efficacy of NRM treatments or the patient’s need for those treatments unless that statement is made by a qualified medical practitioner
    • making an agreement with a patient for the supply of medications or medical services for the treatment of male sexual dysfunction without providing a written statement of the terms of the agreement and termination rights;
    • making an agreement with a patient for the supply of medications or medical services for the treatment of male sexual dysfunction unless that agreement has a cooling off period and can be terminated by giving 14 days’ notice.
  • restraining Mr Vaisman from continuing his main role in the business of NRM which was involved in the unconscionable conduct for a period of seven years
  • requiring corrective advertising.
  • For further enquiries contact the Media Team on 1300 138 917

END UPDATE

It also emerged in a January 2011 article in The Age Business section, that a “silent partner” in this failed venture is behind Astarra Strategic Fund, which resulted in Australia’s largest superannuation theft. In fact the “partner” is a network of “dodgy brokers” headed up by John Flader the supposed master swindler of the Astarra theft.

Meanwhile the AMI swindle rolls on. The last notable action involving AMI was a directions hearing in Melbourne in October 2011. A feature of the pre NRM AMI if you will, was the inability for customers to cancel their contract until they’d tried every single treatment AMI could dream up. Whilst boasting high success and ensuring that every unsatisfied customer received a full refund, the reality was virtual theft from customer bank accounts.

The only way to stop AMI withdrawing money from an account is to have the account closed and another opened with new details.

Recently AMI wheeled out a Debt Collection department. Their job is to chase up clients who still “owed money” on the futile contracts before AMI went into voluntary liquidation. The problem here is any liabilities accrued by AMI then become those of the liquidator. Not AMI and certainly not NRM.

Despite “NRM Corporation Trading As AMI” actually not being liable for any so-called contract debts the threats to “go legal” and destroy any non-compliant customer credit ratings is standard. For 15% of the outrageous contract total NRM will allow clients off the hook. But only if clients bring up the possibility first, or happen to laugh heartily down the phone at NRM’s new take on post liquidation liability. They will not inform customers who don’t raise dissent. From the ACCC site:

NRM patients are required to provide 30 days’ written notice to NRM to terminate the contract and must also pay a number of fees including a fixed administrative fee of 15 per cent of the original contract price. The ACCC alleges that each of the fees had the effect of penalising a consumer who gave notice of termination and therefore causing a significant imbalance in the parties’ rights under the contract.

There are cases where clients – who are in fact patients – eventually consult their GP and then a urologist, cardiologist, oncologist or another specialist. Information is passed to AMI specifically stating they can do nothing to improve the condition. Indeed many “treatments” are dangerous and have exacerbated serious medical problems for months. AMI go through the motions of ensuring a refund for expenses paid. They have been known to then debit bank accounts to the tune of the total contract cost.

Of course, there is no written contract that clients sign outlining any of these eventualities. The famed refunds are a scam from day one because they do not exist. There simply is no document wherein lies any customer contract. Clients should remember this in the event of AMI Debt Collectors calling to terrify. You are thus still waiting on the official contract.

If clients have been clever enough to realise the scam and ditch their bank account AMI Debt collection ring to intimidate, threaten and bully. To “go legal” as they say. Exactly what ageing, ill and often pension dependent patients need.

At this point getting consumer and legal advice, alerting and perhaps lodging a complaint with the ACCC and making some well advised choices about taking that 15% option is in order. After you’re certain that they can effect your credit rating. Remember that AMI are engaged in unconscionable conduct, and NRM intentionally set out to engage in unconscionable conduct.

There is no evidence the so-called Debt Collection isn’t another scam, and it alone is unconscionable conduct by extension. The ACCC will confirm this. As I note above, any debt AMI accrued pre June 2011 is not legally theirs to recover. With luck they will soon be shut down and prosecuted. If contacted clients should not hesitate to summarise this ACCC entry.

Medications sold via their contracts include SSRI’s like fluoxetine (Prozac), paroxetine (Aropax or Paxil), escitalopram (Lexapro), sertraline (Zoloft) etc. These were introduced over the late 1970’s – 1980’s with Lexapro introduced some years later.

AMI also favour old style tricyclic antidepressants such as Clonipramine. This cutting edge technology has been around since the 1950’s with clonipramine added to common tricyclic antidepressants in the 1960’s. The pain killer Tramadol is another.

Their super advanced Path Breaking Research and Development also includes, as mentioned, the Parkinson’s drug apomorphine via lozenge, nasal spray or tongue strip. Apomorphine has been around since the 1940’s.

Why these drugs? SSRI’s and tricyclic antidepressants have a side effect in prolonging time to ejaculation. This effect may persist or may be prove to be transient. Remembering the conditions they are prescribed for, and the side effects they already carry I’ll leave you to consider the value of such off-label use.

The shocking aspect here is rather than pay $250.00 per month and be locked in for two years patients could consult their GP and pay around AU $20.00 per month. For those on a pension or any benefit it’s $5.80 per month. No contracts, no threats and no gambling with side effects.

It gets worse. Men have been scammed into a $3,000 contract and bullied into payment long after the penny dropped, only to report they were already on an SSRI reaping any potential benefit of “lasting longer”. In these cases they need not have spent a cent.

A major drawback with SSRI and tricyclic medications is the interaction with some migraine specific medications or even pain killers such as Tramadol. Serotonin Syndrome can be a serious and potentially life threatening reaction to using two or more of these drugs.

A major cause of premature ejaculation is fast neurological response time in pelvic muscles. Guys can even save that $20.00 per month and learn pelvic floor exercises known as Kegel Exercises. Searching for those key words will provide millions of hits. In cases of erectile dysfunction consult your GP to be sure it’s not a more serious problem.

In conclusion do keep in mind that Advanced Medical Institute is neither “advanced” or an “institute”. It’s a scam run by professional parasitic predators who pressure vulnerable, ill and everyday Australian men out of their money. They can offer nothing to improve sexual health – quite the opposite.

In researching for this post I was appalled, infuriated and disgusted by the tactics creatures such as Vaisman use to scheme struggling Aussies who conduct themselves with dignity, strength and poise. To be unwell is one thing, to make a less than ideal decision and be scammed is another. Yet to navigate the resultant quandary with optimism and humour takes a trait I hope I have, somewhere deep inside.

One hopes the ACCC get to use the unconscionable conduct laws with gusto.

  • ACCC resources. Keywords – “Advanced Medical Institute”

http://www.accc.gov.au/search/accc-funnelback/Advanced%20Medical%20Institute

Harm Reduction: How Australia Stopped HIV

In 1985 before the introduction of needle and syringe programmes (NSP) 90% of Australian injection drug users reported sharing injection equipment. By 1994 following introduction of NSPs this figure had fallen to 20%. In 2009 this figure was around 15% possibly reflecting the constant number of distributions from NSP programmes over the previous decade.

One of the most powerful modes of resistance to the spread of HIV/AIDS is Harm Reduction (HR) measures.

In Australia, HR exists as one of three pillars of Harm Minimisation (HM) – our official illicit drug control policy. The other two pillars are Supply Reduction and Demand Reduction. Reduction in supply receiving the lions share of funding directs energy at reducing international and domestic supply. Reduction in demand receiving less funding delivers programmes and initiatives designed to reduce the demand for drugs within communities.

Harm Reduction receiving the least funding from the HM pile targets the harm to individuals that eventuates from behaviour. HR has always drawn condemnation from conservative groups because of the association with drug use and sex. Initially men who have sex with men (MSM). Then later through maximal exploitation of drug using pop culture. Nonetheless, study after study comparing countries and districts within countries to have implemented HR or not done so, show a stunning success in favour of HR.

This post will look almost exclusively at IV drug use. HR for Injection Drug Users (IDU) includes provision of clean needles and sterile water, swabs, sharps containers for disposal and specialised filters capable of removing bacteria. Opioid Substitution Therapy (OST) including methadone and buprenorphine and safe injecting facilities are pivotal aspects of HR. Heroin on prescription is not available in Australia but has shown unprecedented success as a HR measure where it has been implemented.

Despite the evidence supporting HM as an effective policy and the reality that Supply Reduction [law enforcement] is the most highly funded pillar, Aussies are still subject to notions such as “Tough on drugs” and code words such as Drug Free Australia’s Harm Prevention. Intuitively it sounds fine. Why minimise harm if you can prevent it?

Yet on examination “harm prevention” is the abandonment of HM for the reintroduction of Just Say No approaches. Known to have had deleterious effects on self esteem, no effect on lowering drug use and providing the field upon which drug use flourished, Just Say No quite simply failed, and failed Epically. Today of course, skeptics are well aware of how beliefs and behaviours are reinforced through attacking them. Harm Prevention even more so is code for punitive, custodial and forced behaviour control.

It is at times perplexing as to why so much energy is spent on attacking HM entirely. Supply Reduction however is based in part upon the reality that people want, seek, use and enjoy illicit drugs. Education to accompany this is open and honest – not promotion of illicit drug use . Yet to the conservative mind the idea that their children, friends or the community at large is the demographic from which drug demand comes, is morally untenable.

With HR it is aspects of this pillar that equally cannot be accepted. To the conservative mind, just as condoms cause AIDS and promote sexual promiscuity so too do clean needles, safe injecting facilities and safe injecting education encourage drug use. Drug Free Australia write:

We need to re-focus our drug policy and practice on an approach that prioritises primary prevention, if we are to see any real change in the health and wellbeing of our current and future generations of young people. We need to acknowledge that Australia has one of the highest rates of drug use, because of a priority on Harm Minimisation rather than Harm Prevention, and we now need to take a leaf out of the books of the policy makers in the UK and United States. Both these countries have given greater emphasis to prevention initiatives, while still aiming to help people who are drug dependent, to recover.

The towering dishonesty inherent in this nonsense is typical of the tactics used by DFA in what has become over just a few years, one of the most immoral lobbying groups on the illicit drug landscape. Australia has high levels of cannabis use and abuse. This is handy in arguing that we have high drug use generally. A synopsis of the above is simply: Harm Minimisation has caused Australia to have one of the highest drug use levels in the world. We should be doing what America and the UK do.

The UK get a mention because they reclassified cannabis to a Class B (like speed/other amphetamines) from a Class C drug and punish users accordingly. Of 2.3 million USA prisoners in 2010, over 65% or 1.5 million meet DSM IV medical criteria for substance abuse or addiction. On top of this another 458,000 have a history that meets DSM IV criteria for addiction, were under the influence when they committed their crime, committed a crime to finance the purchase of drugs or were incarcerated for a drug law violation.

Between 1960 and 1990 official crime rates in Finland, the USA and Germany were similar. Incarceration in Finland dropped 60%, remained stable in Germany and quadrupled in the USA, driven primarily by drug convictions.

Today around around 80% of USA prisoners are incarcerated due to illicit drugs. 11% are receiving some type of “treatment”. The last thing Aussies need is a dose of the USA nightmare.

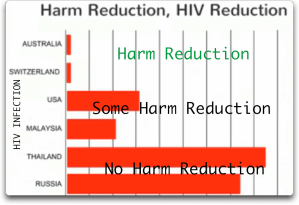
What of the impact of changing our strategy on HIV and consequently other types of blood borne virus transmission? The graph below is from a TED talk by Sereen El-Feki, vice-chair of the Global Commission on HIV and the law:

HIV infection in Injection Drug Users

Whilst Thailand and Russia have ignored Harm Reduction and Australia and Switzerland have embraced it the USA and Malaysia employed only some Harm Reduction techniques. Should Australia embrace USA tactics our prison population will explode, HIV infection in IV drug users will increase by about eight times the present rate and treatment – presently some of the best in the world with plunge to 11%. The cost to the public health purse would simply gut present programmes and destroy any hope of improvement for say, dental, mental health, public hospital care, nursing home care etc.

There is a 4 minute out-take from Sereen El-Feki’s TED talk in April this year below. Or download MP3 here.

The first case of AIDS was reported in Australia in 1983. At that time morbidity rates to rival World War II were expected. Following the innovative approach of HR, levels of infection in all demographics fell from 2,500 per year to 500 in the decade following inception of HR. This infection rate has remained stable.

At the time, initiation of clean needle supply contravened the states Drug Offensive which, already highly criticised, had regrettably escalated drug use and criminalisation via the failed “Just Say No” approach. The pilot programme ran from St. Vincents Drug and Alcohol Service on November 13 1986. It was run in the suburb of Darlinghurst. An evaluation recommended they should be adminstered by social workers, drug agencies, pharmacies, medical professionals and urged:

The urgent widespread introduction of needle exchange programmes in all states and territories

There needed to be an amendment to the Drug Misuse and Trafficking Act following which NSW pharmacies sold “anti-AIDS kits”. By mid 1989 there were 40 public outlets run across Sydney. By 1994 there were 250 outlets run by NGOs, government agencies and pharmacists distributing 3.5 million syringes annually. For the year 1993-1994 10.3 million syringes were distributed across Australia. The USA with 15 times the population of Australia distributed 8 million syringes in 1994-1995.

More comprehensive analyses refuted the concerns of increasing drug use. No increase in drug use was seen in any country that had instigated needle exchange and more so, attendance at rehabilitation and abstinence programmes had increased. Australia’s Commonwealth Department of Health (now Dept. of Health and Ageing) estimated that 25,000 cases of HIV were averted in the 12 years from 1988 – 2000 due to needle exchange alone (page 10 – 3.5.3).

The infection rate among Aussie IDU sat at around 3%. Users who were also MSM had an infection rate of 27%. In Russia where HR for drug users was denied, the figure for IDU was between 75 and 90%. One study in 1997 looked at 81 European cities with and without needle exchange programmes. Seroprevalence (measured from the presence of HIV within blood taken from used syringes) increased 5.9% annually in cities without clean needle distribution, and decreased 5.8% in cities with needle exchange.

In an astonishing comparison, Edinburgh with no NSP experienced a 65% HIV infection rate amongst IDU. Glasgow, less than an hours drive away and with NSP experienced a 4.5% increase in HIV infection amongst IDU. The one issue Australia faced was return of used syringes. Users were placing them in sharps bins. Yet to return any syringes to Exchanges meant risking being questioned by police. A used syringe is evidence of illicit drug use and this acted as a disincentive to return items for safe disposal.

Of note however is that fears and front page headlines of beach goers and joggers stepping on syringes and undergoing “agonising waits” for blood tests to be cleared of HIV infection are out of proportion. HIV dies very quickly once outside the body and syringes on beaches have been discarded into drains, washed out to sea and then beached. Nonetheless despite the absence of actual transmission it is an unpleasant experience which can be lessened by removing all offences for possession of a used syringe.

Clearly, Australia’s decision to take the necessary steps and bring together members of drug using demographics, gay rights advocates and prostitutes collectives and allow them to consult upon and shape this programme was one of it’s greatest public health initiatives ever.

Between 2000-2009 NSPs have averted 32,050 new cases of HIV and 96,666 Hepatitis C infections. Needles distributed increased from approximately 27 million to 31 million in that decade. For every one dollar invested, four dollars have been saved. 140,000 Disability Adjusted Life Years were gained over the same decade.

Still, conservative biblical fundamentalist group Drug Free Australia boldly inform us that Return On Investment is quite wrong and should show an expense. In earlier posts you can access from the tag on the right, I highlight how they cherry pick phrases and select data out of context. At other times they simply dismiss WHO findings based solely on the reviews of just one Swedish researcher, Dr Kerstin Käll.

So to be very clear, Dr Kerstin Käll, working for the Swedish government who are dodging UN demands to establish more Needle Exchanges and accelerate HR or remain in breach of the international right to health, conducted no research but criticised methodology that was favourable of NSP success. Her own research argues regular testing for HIV is more of a prevention – yes prevention – than clean needle supply.

It’s easy to get confused because whilst Käll supports NSP programmes as reducing hepatitis C in prisons DFA refute any change in HCV attributable to NSP programmes… anywhere. They also lobby stridently against the establishment of needle exchange in Australian prisons. Of course, despite the evidence above they insist the impact of NSP on HIV is “inconclusive”.

Ultimately it’s irrefutable how successful Harm Reduction has been in controlling the spread of blood borne viruses. Paramount amongst these is HIV, Hepatitis C and Hepatitis B. The most significant and visionary measure to now apply would include steps to decriminalisation and regulation.

Today however, this is where Australia is falling behind.